
Why Choose Minimally Invasive Arthroplasty?
Joint replacement can restore movement, reduce pain, and return patients to ordinary routines. However, the surgical route matters. Minimally invasive arthroplasty uses smaller access pathways and tissue-sparing techniques around the hip or knee. The goal is practical: less muscle disruption, earlier mobility, and a smoother return to daily activities.
Evidence remains encouraging, but it is not absolute. The American Joint Replacement Registry’s 2023 Annual Report shows the continuing growth and long-term monitoring of hip and knee replacement care in the United States. Similarly, the UK National Joint Registry’s 20th Annual Report tracks millions of procedures and highlights the importance of implant survival, revision rates, and patient outcomes. These reports support careful measurement, not simple marketing claims. A smaller incision alone does not guarantee a better result.
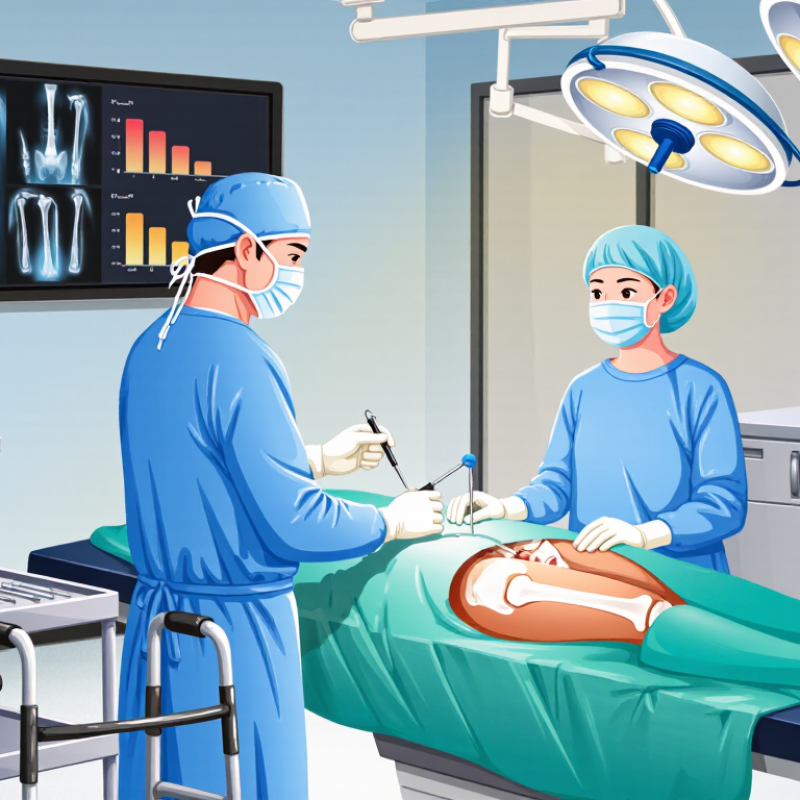
Experienced surgeons consider anatomy, bone quality, body weight, previous operations, and rehabilitation support before recommending Minimally invasive arthroplasty. A patient may stand beside the bed sooner, with a walker and a carefully checked dressing, yet recovery still varies. Some patients progress quickly. Others need more time.
The AAOS emphasizes shared decision-making and evidence-based surgical selection. That principle matters here. Minimally invasive methods may reduce early pain or hospital time for selected patients, but long-term advantages can be less consistent across studies. The technique also demands precise positioning, strong training, and reliable postoperative care. Outcomes depend on the whole pathway.
The evidence is promising. It still needs humility. Choosing this approach should mean choosing appropriate care, not simply choosing smaller scars.
What Is Minimally Invasive Arthroplasty?
Minimally invasive arthroplasty is joint replacement performed through a smaller incision and with less disruption to surrounding muscles and soft tissues. The goal is not simply a shorter scar. Surgeons also aim to reduce tissue trauma, control bleeding, and support earlier movement when appropriate. During the procedure, damaged joint surfaces are removed and replaced with carefully selected components. The exact technique depends on the joint, bone quality, anatomy, and the surgeon’s training. It is not a magic shortcut. A smaller incision does not guarantee less pain or faster recovery for every patient.
Tips: Ask how the procedure changes muscle handling, pain control, hospital stay, and rehabilitation. Request clear information about possible complications, including infection, blood clots, stiffness, nerve irritation, or implant problems. Bring your medication list and mention previous operations or medical conditions. Good preparation matters. So does realistic planning.
Recovery often begins with assisted walking and simple exercises soon after surgery. Some people regain function quickly, while others need several weeks or months. Age, fitness, weight, home support, and adherence to therapy can influence progress. My own reflection is that “minimally invasive” can sound more certain than it really is. The operation remains major surgery, and careful patient selection is essential. A qualified orthopedic specialist should explain whether this approach fits your anatomy, health status, and daily goals.
Why Choose Minimally Invasive Arthroplasty? - What Is Minimally Invasive Arthroplasty?
An evidence-based overview of the technique, potential advantages, limitations, and patient considerations
| Data Dimension | Evidence-Based Information | Clinical Significance |
|---|---|---|
| Definition | Minimally invasive arthroplasty is joint-replacement surgery performed through a smaller or less disruptive surgical approach, with the goal of reducing damage to surrounding muscles, tendons, and soft tissues. | The technique is intended to support tissue preservation, but it is still a major operation involving removal and replacement of damaged joint surfaces. |
| Common procedures | The approach is most commonly discussed in relation to total or partial hip replacement and total knee replacement. It may also be used in selected shoulder and other joint-replacement procedures. | The appropriate approach depends on the joint, the patient’s anatomy, the surgeon’s experience, and the complexity of the reconstruction. |
| Incision size | Incisions are generally smaller than those used in some traditional approaches, but there is no single universally accepted incision length. Size varies by joint, body habitus, implant requirements, and surgical technique. | A smaller skin incision does not automatically mean less internal tissue disruption or a faster recovery. |
| Muscle and soft-tissue handling | Some minimally invasive approaches use muscle-sparing or tissue-sparing pathways. The amount of muscle detachment and soft-tissue disruption differs substantially between approaches. | Preserving soft tissue may help early function, but safe exposure and accurate implant positioning remain the primary goals. |
| Potential early benefits | Studies have reported possible reductions in early postoperative pain, blood loss, and hospital stay in selected patients and procedures. The size of these benefits is inconsistent across clinical studies. | Early advantages may be meaningful, but they should be weighed against the surgeon’s ability to perform the procedure safely and accurately. |
| Hospital stay | Many joint-replacement patients now leave the hospital on the day of surgery or within 1–3 days when medically appropriate. Length of stay depends on mobility, pain control, home support, and overall health—not only on incision size. | Enhanced recovery programs, physical therapy, anesthesia, and discharge planning can influence recovery as much as the surgical approach. |
| Blood loss and transfusion | Less soft-tissue disruption may reduce visible blood loss in some procedures, although modern blood-management protocols have also substantially reduced transfusion requirements in joint replacement. | Preoperative anemia treatment, medication management, and surgical technique all contribute to blood-loss control. |
| Recovery and rehabilitation | Patients may regain walking ability and daily function quickly, but recovery commonly continues for several weeks to months. Strength, swelling, balance, and joint motion may improve gradually. | A minimally invasive approach does not eliminate the need for structured rehabilitation or activity restrictions. |
| Long-term implant outcomes | When the implant is correctly positioned and the procedure is appropriately selected, long-term outcomes can be comparable to those of conventional approaches. The approach itself has not consistently been shown to provide superior implant longevity. | Component alignment, fixation, implant quality, patient factors, and postoperative care are important determinants of durability. |
| Potential risks | Risks include infection, blood clots, nerve or blood-vessel injury, fracture, dislocation in hip replacement, stiffness, persistent pain, implant loosening, and revision surgery. Limited surgical exposure may increase technical difficulty in some cases. | Reducing incision length does not remove the standard risks of arthroplasty and may introduce additional technical challenges for selected patients. |
| Patient selection | Suitability depends on diagnosis, bone quality, joint deformity, previous operations, body composition, muscle condition, medical status, and the surgeon’s experience with the selected approach. | There is no single approach that is best for every patient. Individual assessment is essential. |
| When conventional surgery may be preferred | A conventional or more extensile approach may be appropriate when there is severe deformity, complex revision surgery, major bone loss, difficult anatomy, fracture, or a need for wider exposure. | Wider exposure can improve visualization and may reduce the risk of component malposition or unintended tissue injury in complex cases. |
| Role of surgeon experience | Clinical outcomes are influenced by training, case volume, surgical planning, patient selection, and the team’s rehabilitation protocol. A smaller incision alone is not a reliable measure of quality. | Patients should discuss the surgeon’s experience with the specific procedure, expected benefits, possible complications, and alternatives. |
| Best-supported expectation | Minimally invasive arthroplasty may offer faster early recovery for selected patients, but evidence does not establish universal superiority over conventional approaches for every outcome or every patient. | The most appropriate choice balances early recovery goals with surgical safety, accurate reconstruction, long-term function, and individual medical needs. |
Important: The expected benefits and risks vary by joint, surgical approach, patient characteristics, and clinical setting. A qualified orthopedic surgeon should determine whether minimally invasive arthroplasty is appropriate for an individual patient.
Related Posts
-

China Top 10 Prosthesis Fixation Methods Suppliers
-
Top 10 Total Joint Replacement Care Tips for Global Buyers
-
What Are Bone Preservation Implants and How Do They Work?
-
7 Tips on Knee Replacement Advances for Buyers
-
Best Research on Implant Survivorship Rates Worldwide?
-

China Top 10 Minimally Invasive Arthroplasty Techniques You Should Know?